
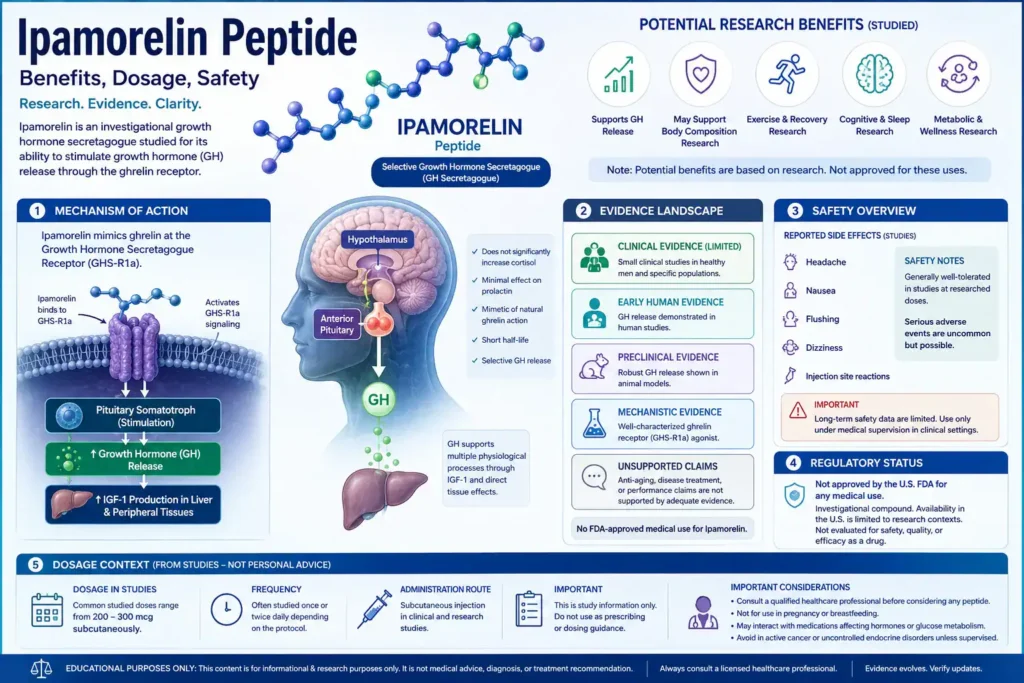
Ipamorelin peptide is an investigational growth hormone secretagogue discussed for its effects on growth hormone release, GH-axis signaling, body composition claims, and postoperative gastrointestinal research. This educational article reviews what published literature and regulatory sources say about ipamorelin, without giving personalized medical advice or recommending use.
- Ipamorelin is a synthetic pentapeptide described by the National Cancer Institute as a ghrelin mimetic that binds the growth hormone secretagogue receptor and stimulates growth hormone release from the pituitary gland 1.
- Ipamorelin is discussed as a selective growth hormone secretagogue because early pharmacology work found GH release without the same cortisol and ACTH stimulation seen with some older growth hormone releasing peptides 2.
- Human research includes pharmacokinetic and pharmacodynamic studies in healthy volunteers and a phase 2 postoperative ileus trial, but these studies do not establish broad wellness, anti-aging, fat loss, or muscle growth benefits 3, 4.
- Ipamorelin has no FDA-approved drug product or approved labeled indication in the United States, and FDA compounding reviews have raised concerns about immunogenicity, aggregation, peptide impurities, and limited safety data for proposed injectable routes 5, 6.
- Dosage information for ipamorelin should be interpreted as study context, not personal medical guidance. Published studies used controlled protocols such as intravenous infusion in healthy volunteers and postoperative dosing in a monitored clinical trial 3, 4.
- Claims about better sleep, lean muscle, fat loss, tissue repair, energy, or healthy aging are evidence-sensitive. Some are biologically plausible through the GH and IGF-1 axis, but strong ipamorelin-specific human outcome data are limited 10, 12.
Related dosage pages: For vial-specific concentration, reconstitution, and measurement examples, see Ipamorelin (5 mg Vial) Dosage Protocol and Ipamorelin (10 mg Vial) Dosage Protocol. Each linked protocol remains a separate reference because vial strength changes concentration and syringe-unit calculations.
Fast Answer
Ipamorelin peptide is a synthetic growth hormone secretagogue that mimics ghrelin signaling and stimulates growth hormone release through the growth hormone secretagogue receptor 1, 2. It is often searched for body composition, fat loss, muscle growth, sleep, recovery, and anti-aging claims, but published human evidence is limited. Ipamorelin is not FDA-approved, and FDA compounding reviews cite safety uncertainties, including peptide-related impurities, aggregation, immunogenicity, and limited data for proposed injectable use 5, 6.
Evidence basis note: This page uses regulatory documents, drug labels, clinical studies, clinical-trial registry information, and peer-reviewed literature as its evidence base. Claims that are common online but not supported by reliable human data are treated as preliminary, unsupported, or unverified rather than established benefits.
What Is the Ipamorelin Peptide?
Ipamorelin is a synthetic pentapeptide growth hormone secretagogue studied for its ability to stimulate GH release through ghrelin-receptor signaling, rather than as an approved medication for wellness, body composition, or anti-aging use 1, 2.
Peptide Classification as a Selective Growth Hormone Secretagogue
Ipamorelin belongs to the growth hormone secretagogue category, a class of compounds that stimulate growth hormone secretion through mechanisms distinct from administering synthetic human growth hormone directly. The National Cancer Institute describes ipamorelin as a pentapeptide and ghrelin mimetic that binds the growth hormone secretagogue receptor, also called GHSR 1.
The word “selective” is important. In early pharmacology research, ipamorelin stimulated GH release in vitro and in vivo while showing less ACTH and cortisol activity than some earlier GHRP compounds at tested doses 2.
How Ipamorelin Relates to Ghrelin and the Pituitary Gland
Ipamorelin relates to ghrelin because ghrelin is an endogenous hormone that activates the growth hormone secretagogue receptor, and ipamorelin was developed to mimic parts of that signaling pathway 1. The pituitary gland is central because GH is released from pituitary somatotroph cells after upstream hypothalamic and receptor-mediated signals.
This GH-axis context explains why ipamorelin is often discussed alongside GHRH, IGF-1, CJC-1295, tesamorelin, and other growth hormone secretagogues. Those comparisons are useful for understanding mechanisms, but they do not prove that ipamorelin has the same clinical evidence or regulatory status as approved peptide drugs.
Why Ipamorelin Is Discussed in Peptide Therapy
Ipamorelin is discussed in peptide therapy because it can increase growth hormone release in controlled research settings, and growth hormone biology is linked to body composition, metabolism, bone, muscle, and quality-of-life outcomes in true adult growth hormone deficiency 10, 11.
That discussion requires caution. Evidence for diagnosing and treating adult GH deficiency comes from formal endocrine evaluation and approved therapies, not from online wellness protocols using unapproved peptides 10.
How Does Ipamorelin Peptide Work?
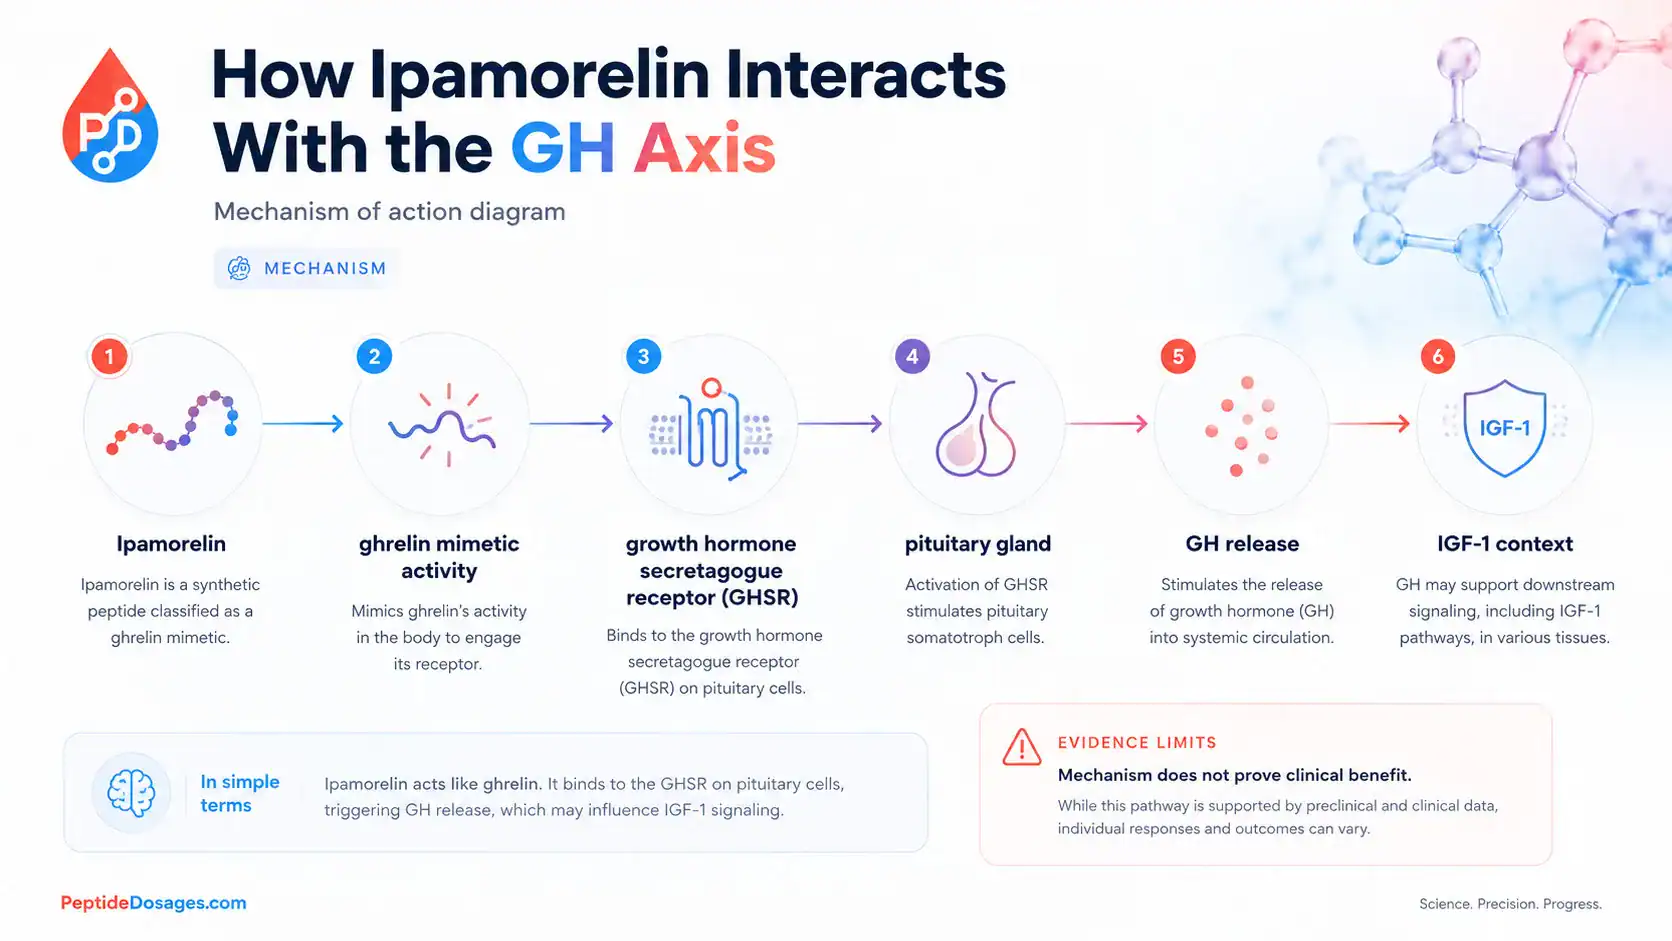
Ipamorelin peptide works by activating the growth hormone secretagogue receptor, which can trigger pituitary growth hormone release and downstream IGF-1 signaling under studied conditions 1, 2.
Ghrelin Receptor Agonist Activity
Ipamorelin acts as a ghrelin mimetic at the growth hormone secretagogue receptor, a receptor involved in GH release and expressed in the brain and other tissues 1. This receptor-level activity is the pharmacologic reason ipamorelin is classified as a growth hormone secretagogue rather than as synthetic HGH.
A human pharmacokinetic-pharmacodynamic study modeled ipamorelin exposure and GH response after intravenous infusion in healthy male volunteers, showing that GH response was measurable in a controlled dose-escalation setting 3.
Growth Hormone Pulses, GH Release, and IGF-1
Ipamorelin stimulates GH release rather than replacing GH directly 1, 2. GH then influences IGF-1 production, especially through hepatic signaling, although GH and IGF-1 responses depend on dose, route, timing, age, endocrine status, and study population.
A review of growth hormone secretagogues notes that this drug class can promote pulsatile GH release, but also emphasizes that long-term, rigorously controlled studies remain limited for many secretagogues 12.
Mechanism of Action: GH, GHRH, and Hormone Selectivity
Ipamorelin’s mechanism is best understood as GHSR-mediated GH stimulation that intersects with the broader GHRH and somatostatin-regulated growth hormone axis 1, 2.
Growth Hormone Secretagogue Receptor Signaling
Growth hormone secretagogue receptor signaling is a receptor-mediated pathway that can increase pituitary GH secretion after activation by ghrelin-like compounds 1. Ipamorelin was developed as an oligopeptide agonist in this pathway, with early evidence showing GH release in animal and laboratory models 2.
Mechanism is not the same as clinical benefit. A compound can change a hormone biomarker, such as GH or IGF-1, without proving durable improvement in body composition, sleep quality, tissue repair, or energy levels.
Cortisol or Prolactin Effects Compared With Older GHRPs
Ipamorelin was described in early literature as more selective for GH release than some older growth hormone releasing peptides, including GHRP-6, because tested doses did not show the same ACTH or cortisol stimulation 2.
This selectivity does not mean ipamorelin has no endocrine risks. FDA reviewers have noted that products stimulating GH release can raise concerns related to glucose intolerance, diabetes risk, cardiovascular effects, tissue growth, neoplasms, and immune responses 5.
What Is Ipamorelin Peptide Used For or Studied For?
Ipamorelin has been studied for GH release and postoperative ileus, but it is not FDA-approved for growth hormone deficiency, fat loss, muscle growth, anti-aging, sleep, or wellness use 4, 5, 6.
Growth Hormone Deficiency and Clinical Research Context
Ipamorelin has been evaluated in the context of growth hormone stimulation, but adult growth hormone deficiency is a medical diagnosis that usually requires appropriate clinical context and GH stimulation testing unless there is a proven genetic or structural lesion 10.
Guidelines on adult GH deficiency describe potential benefits of approved GH therapy in severe deficiency, including body composition and quality-of-life outcomes, but those recommendations do not establish ipamorelin as an approved treatment 10, 11.
Body Composition, Visceral Fat, and Metabolic Endpoints
Ipamorelin is commonly discussed for body composition, visceral fat, lean muscle mass, and fat loss because GH and IGF-1 biology intersect with metabolism and tissue remodeling. The limitation is that ipamorelin-specific human outcome evidence for these endpoints is not comparable to approved-drug data.
Tesamorelin is a useful contrast. FDA labeling describes tesamorelin as a growth hormone releasing factor analog approved to reduce excess abdominal fat in adults with HIV and lipodystrophy, while also stating that it is not indicated for weight loss management 7.
Potential Benefits of Ipamorelin Peptide
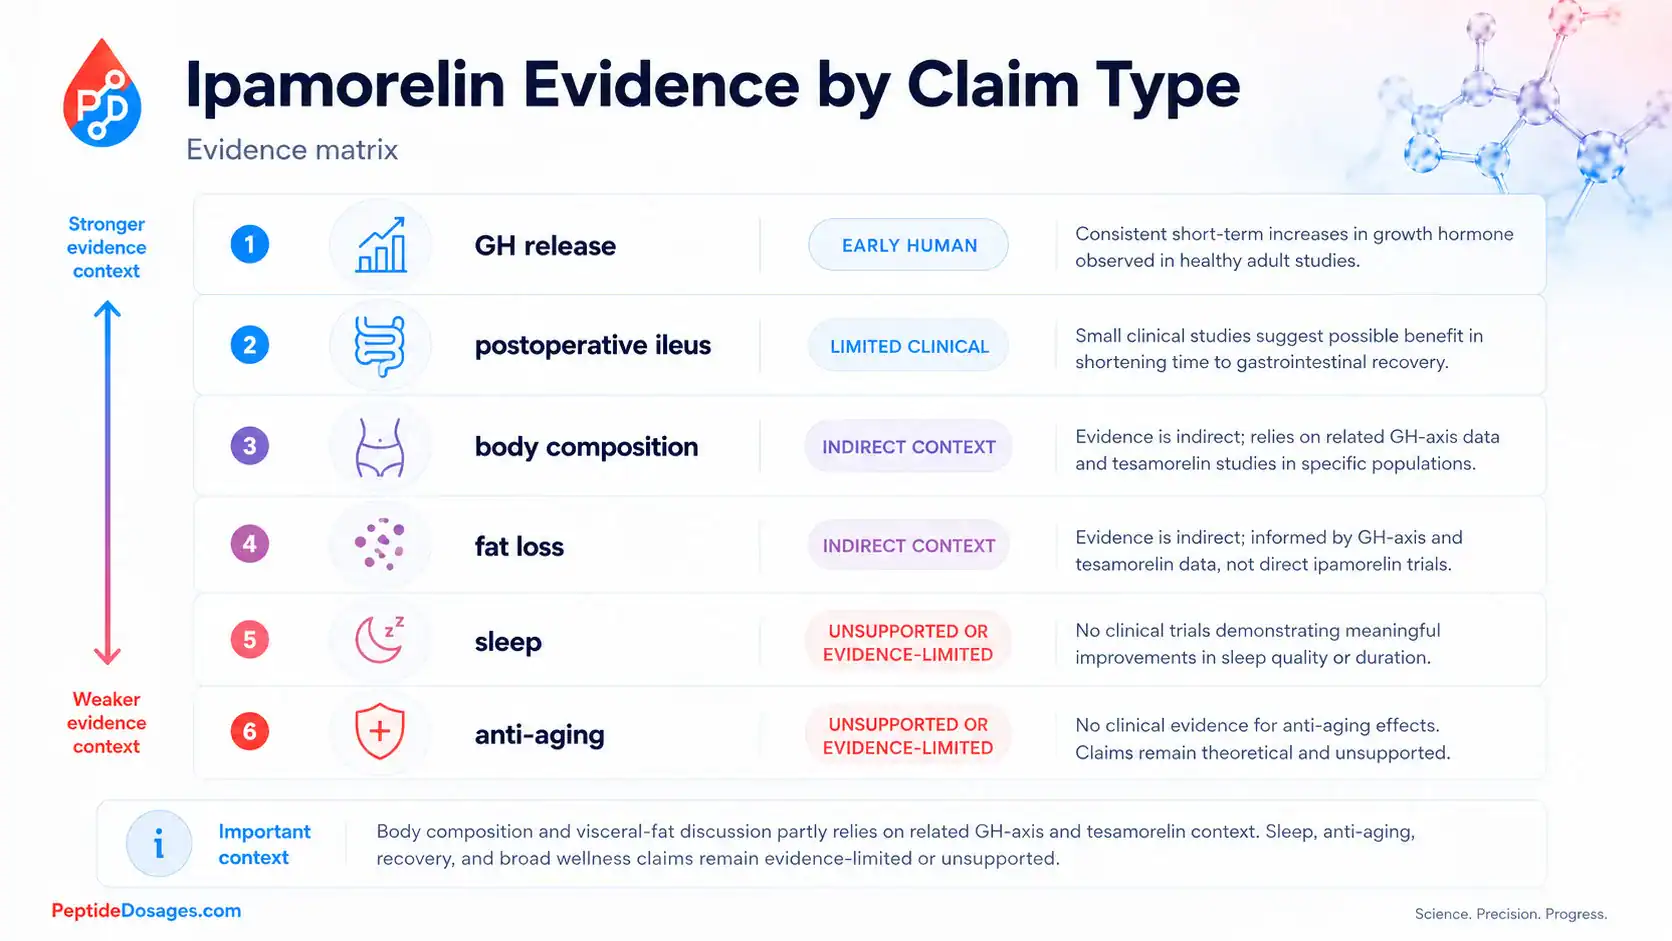
Potential benefits of ipamorelin peptide are mostly inferred from GH-axis biology, early human hormone-response data, preclinical work, and online claims, not from strong long-term trials proving broad therapeutic outcomes 3, 4, 12.
Benefits of Ipamorelin Commonly Discussed Online
Commonly discussed benefits of ipamorelin include fat loss, lean muscle, muscle growth, better sleep, recovery, tissue repair, energy, and anti-aging effects. These claims should be separated from the narrower published evidence showing GH release and limited clinical trial testing.
A practical evidence filter is helpful:
| Claim Area | What Has Been Studied | Evidence Level | What It Can and Cannot Show |
|---|---|---|---|
| GH release | Human volunteer PK/PD studies measured GH response after controlled infusion 3. | Early human | Shows hormone response, not long-term clinical benefit. |
| Postoperative ileus | Phase 2 trial tested IV ipamorelin after bowel resection 4. | Clinical, limited | Did not show statistically significant improvement in primary recovery endpoints. |
| Body composition | GH biology and approved GH-related therapies affect body composition in specific diagnosed conditions 10, 11. | Indirect clinical | Does not prove ipamorelin improves body composition in general wellness use. |
| Fat loss and visceral fat | Tesamorelin has an approved visceral-fat indication in HIV lipodystrophy 7. | Approved for tesamorelin, not ipamorelin | Useful comparison, but not transferable proof for ipamorelin. |
| Anti-aging and wellness | GH secretagogue claims appear in wellness contexts; long-term evidence is limited 11, 12. | Unsupported or preliminary | Does not establish anti-aging benefit. |
Full View
Lean Muscle, Muscle Mass, and Muscle Growth Claims
Ipamorelin is often linked to lean muscle and muscle growth because GH and IGF-1 participate in anabolic signaling. That mechanism is biologically plausible, but ipamorelin-specific human trials have not established a reliable muscle-building outcome for healthy adults.
Adult GH deficiency literature shows that approved GH replacement can affect body composition in confirmed severe deficiency, but the Endocrine Society guideline is not an endorsement of ipamorelin for healthy people or non-diagnosed wellness use 10.
Fat Loss, Body Weight, and Body Composition Changes
Ipamorelin fat loss claims remain evidence-limited. The strongest approved-drug comparison in this lane is tesamorelin for excess abdominal fat in HIV-associated lipodystrophy, not ipamorelin for general fat loss or body weight management 7.
This distinction matters for readers. A related peptide drug can have an approved indication while ipamorelin remains unapproved and less studied for the same general outcome category.
What Sleep, Recovery, Wellness, and Healthy Aging Claims Are Made?
Sleep, recovery, wellness, and healthy aging claims around ipamorelin are common but not strongly established by long-term ipamorelin-specific human trials 11, 12.
Better Sleep, Sleep Quality, and Energy Levels
Growth hormone secretagogues have been discussed in relation to sleep and GH pulsatility, but class-level discussion is not the same as proof that ipamorelin improves sleep quality or energy levels in typical users 12.
Sleep and energy are also nonspecific outcomes. They can be affected by endocrine disease, medications, nutrition, sleep disorders, stress, and other medical conditions that require diagnosis rather than peptide self-experimentation.
Tissue Repair and Regenerative Medicine Claims
Tissue repair and regenerative medicine claims for ipamorelin are largely mechanistic or extrapolated from GH biology. Preclinical work can help explain pathways, but it cannot establish human tissue-repair benefit by itself.
The same caution applies to “recovery” claims. A measurable GH pulse does not automatically translate into faster healing, improved injury recovery, or better clinical outcomes.
Why Anti-Aging Benefits Need Evidence Grading
Ipamorelin anti-aging claims should be treated as unsupported unless tied to specific, high-quality human outcomes. Endotext explicitly notes that GH use for sports enhancement and anti-aging is strongly discouraged in adult GH deficiency management discussions 11.
Healthy aging is not the same as hormone elevation. The safest evidence-based question is whether a claim is supported by approved labeling, controlled human studies, or only mechanistic reasoning.
What Does Human Research Say About Ipamorelin?
Human research shows that ipamorelin can stimulate GH release in controlled study settings and has been tested in postoperative ileus, but the clinical evidence base remains narrow 3, 4, 16.
Early Human Studies and Clinical Trial Endpoints
A pharmacokinetic-pharmacodynamic study in healthy male volunteers examined 15-minute intravenous infusions across five dose levels: 4.21, 14.02, 42.13, 84.27, and 140.45 nmol/kg 3. That study supports GH-response modeling, not claims about fat loss, muscle growth, sleep, or anti-aging.
A later multicenter, randomized, double-blind, placebo-controlled proof-of-concept trial studied ipamorelin for postoperative ileus after bowel resection 4. DrugBank also lists a completed phase 2 trial for ipamorelin in postoperative ileus, identified as NCT00672074 16.
GH Levels, IGF-1, and Dose-Response Findings
Human volunteer modeling showed that ipamorelin exposure could be linked to GH response after controlled IV infusion 3. The study design supports dose-response interpretation for a hormone biomarker, not a general therapeutic dosing protocol.
GH and IGF-1 also have safety implications. FDA reviewers have noted class-related concerns for products that stimulate GH release, including glucose intolerance, tissue growth, neoplasms, cardiovascular effects, and immunogenicity 5.
Study Size, Duration, and Outcome Limitations
The postoperative ileus study enrolled 117 patients, with 114 analyzed, and used IV ipamorelin 0.03 mg/kg twice daily after surgery until the first tolerated meal, hospital discharge, or postoperative day 7 4. The median time to first tolerated meal was 25.3 hours with ipamorelin and 32.6 hours with placebo, but the difference was not statistically significant 4.
The study reported treatment-emergent adverse events in 87.5% of ipamorelin patients and 94.8% of placebo patients, which suggests tolerability in that specific inpatient trial but does not establish safety for long-term outpatient peptide therapy 4.
What Does Preclinical Evidence Suggest?
Preclinical evidence suggests that ipamorelin can influence GH secretion, gastric motility, and growth-related endpoints in animal models, but animal findings cannot be treated as established human benefits 13, 14.
Animal and In Vitro Findings Related to GH Secretion
Early pharmacology research found that ipamorelin had GH-releasing activity in vitro and in vivo and acted through a GHRP-like receptor pathway 2. Rat research also evaluated subcutaneous ipamorelin over 15 days and reported effects on growth hormone release and longitudinal bone growth endpoints 14.
A rodent postoperative ileus model reported that ipamorelin, described as a ghrelin mimetic, accelerated gastric emptying in that model 13. This was one rationale for later clinical testing in postoperative ileus.
Translational Limits From Models to Human Outcomes
Preclinical models are useful for mechanism and hypothesis generation. They are weaker for predicting human wellness outcomes because dose scaling, route of administration, disease model, species biology, and endpoint selection can all change how results translate.
For ipamorelin, the gap is clear: animal and receptor data support biological activity, while human outcome data remain limited and do not establish broad use for fat loss, anti-aging, muscle growth, or tissue repair.
What Dosage Has Been Studied or Commonly Cited?

Ipamorelin dosage information should be limited to published research protocols and regulatory review context because there is no FDA-approved ipamorelin label that defines an approved dose 5, 6.
What Dosage Has Been Used in Published Studies?
Published human research has used controlled doses under study supervision. In healthy volunteers, ipamorelin was given by 15-minute IV infusion at 4.21 to 140.45 nmol/kg in a pharmacokinetic-pharmacodynamic study 3. In the postoperative ileus trial, ipamorelin was given intravenously at 0.03 mg/kg twice daily after bowel resection until a defined recovery or stopping point 4.
FDA’s compounding review also discussed a nominated proposed concentration of 2000 mcg/mL for subcutaneous injection, while noting the absence of adequate safety data for the proposed route and broader peptide-related concerns 5.
Commonly Cited Protocol Ranges and Their Limits
Commonly cited ipamorelin protocol ranges in wellness settings should not be treated as approved or evidence-based personal dosing. Many such ranges are derived from clinic or internet practice patterns, not FDA-approved labeling or strong human outcome trials.
The most defensible educational approach is to distinguish published study dosing from personal medical instructions. Study protocols describe what researchers tested; they do not tell an individual reader what to take.
Body Weight, Frequency, and Timing Considerations
Body weight, frequency, timing, route, renal and hepatic status, endocrine diagnosis, glucose metabolism, and concurrent therapies can all affect interpretation of GH-axis interventions. Published ipamorelin studies used defined schedules in monitored populations, not generalized self-directed protocols 3, 4.
For personal decisions, readers should discuss endocrine history, goals, alternatives, risks, and monitoring with a licensed clinician rather than applying study doses outside their original context.
How Are Reconstitution and Administration Discussed?
Reconstitution and administration are best discussed as educational concepts for understanding study protocols, not as step-by-step instructions for personal peptide use 5, 6.
Subcutaneous Injection as a Studied Route
Ipamorelin has been studied intravenously in key human studies, while FDA’s compounding review described proposed subcutaneous use and specifically noted limited safety data for that proposed route 3, 4, 5.
Subcutaneous administration is relevant because many peptide discussions involve injection routes, but route matters. IV inpatient dosing, subcutaneous outpatient use, and animal-model dosing are not interchangeable.
Reconstitution, Concentration, and Calculation Concepts
Reconstitution changes concentration, and concentration determines how much solution corresponds to a given mass of peptide. For safety reasons, this article does not provide step-by-step preparation instructions or personal dosing calculations.
The medically responsible point is that concentration, sterility, stability, vial contents, excipients, route, and dose accuracy all affect risk. FDA reviewers specifically identified peptide impurities, aggregation, and immunogenicity as concerns in compounding evaluations 5, 6.
Why Administration Information Is Not Personal Medical Advice
Administration details from literature explain how a study was conducted. They do not create a safe personal protocol.
This distinction is especially important for unapproved peptides. FDA’s Category 2 list notes significant safety concerns for ipamorelin acetate, including immunogenicity, aggregation, peptide-related impurities, unnatural amino acids, serious adverse events reported with IV use for gastric motility, and lack of safety information for other injectable routes 6.
What Side Effects and Safety Issues Are Reported?

Ipamorelin safety information includes clinical-trial adverse events, FDA-reviewed reports, and theoretical GH-axis concerns, but long-term safety for unapproved outpatient use is not established 4, 5, 6.
Reported Adverse Effects and Tolerability Signals
In the postoperative ileus trial, treatment-emergent adverse events occurred in 87.5% of ipamorelin patients and 94.8% of placebo patients, and the authors did not report a statistically significant primary efficacy advantage 4. This safety signal applies to that monitored surgical population and IV protocol only.
FDA’s review of ipamorelin-related substances listed adverse events reported in submitted or reviewed materials, including hypokalemia, insomnia, hyperglycemia, nausea, vomiting, abdominal distention, and deaths for which causality was unclear 5.
Hormone-Related Risks From Increasing GH Levels
Increasing GH levels can have metabolic and tissue-growth implications. FDA reviewers noted concerns for GH-release stimulators that include glucose intolerance, diabetes, tissue growth, neoplasms, cardiovascular effects, and immunogenicity 5.
Approved somatropin labeling also illustrates why GH-axis therapies require medical caution. GENOTROPIN labeling lists contraindications such as acute critical illness, active malignancy, diabetic retinopathy, hypersensitivity, and other specific high-risk settings 8.
Injection-Site and Allergic-Reaction Considerations
Injection-related risks can include local reactions, contamination risk, hypersensitivity, dose error, and problems from product quality. Ipamorelin-specific long-term injection-site safety is not established by an FDA-approved label.
FDA’s compounding risk language is relevant here because compounded peptide preparations may vary in purity, aggregation, stability, and immune response risk 5, 6.
What Contraindications, Cautions, and Interactions Matter?
Ipamorelin has no FDA-approved label defining formal contraindications or drug interactions, so caution should be guided by GH-axis risks, endocrine history, pregnancy status, cancer history, glucose metabolism, and concurrent medications 5, 8, 10.
Endocrine, Metabolic, Cancer-History, and Pregnancy Considerations
People with endocrine disorders, diabetes risk, active or prior malignancy, pituitary disease, pregnancy, breastfeeding, or unexplained symptoms should not interpret ipamorelin content as a substitute for medical evaluation. Approved GH labels and endocrine guidelines show that GH-axis interventions are not casual wellness tools 8, 10.
Because ipamorelin lacks an approved label, special populations are not well characterized. That absence of labeling is itself a safety limitation.
Drugs or Therapies That May Affect Growth Hormone and IGF-1
Concurrent use of growth hormone, secretagogues, GHRH analogs, glucocorticoids, diabetes medications, sex-hormone therapies, and other endocrine treatments can change risk interpretation. Ipamorelin-specific interaction data are limited, so medication review with a clinician is part of responsible evaluation.
This is not just theoretical. FDA reviewers specifically noted concern for GH-release stimulators in relation to metabolic and tissue-growth effects 5.
How Does Ipamorelin Compare With CJC-1295, Tesamorelin, and Related Peptides?
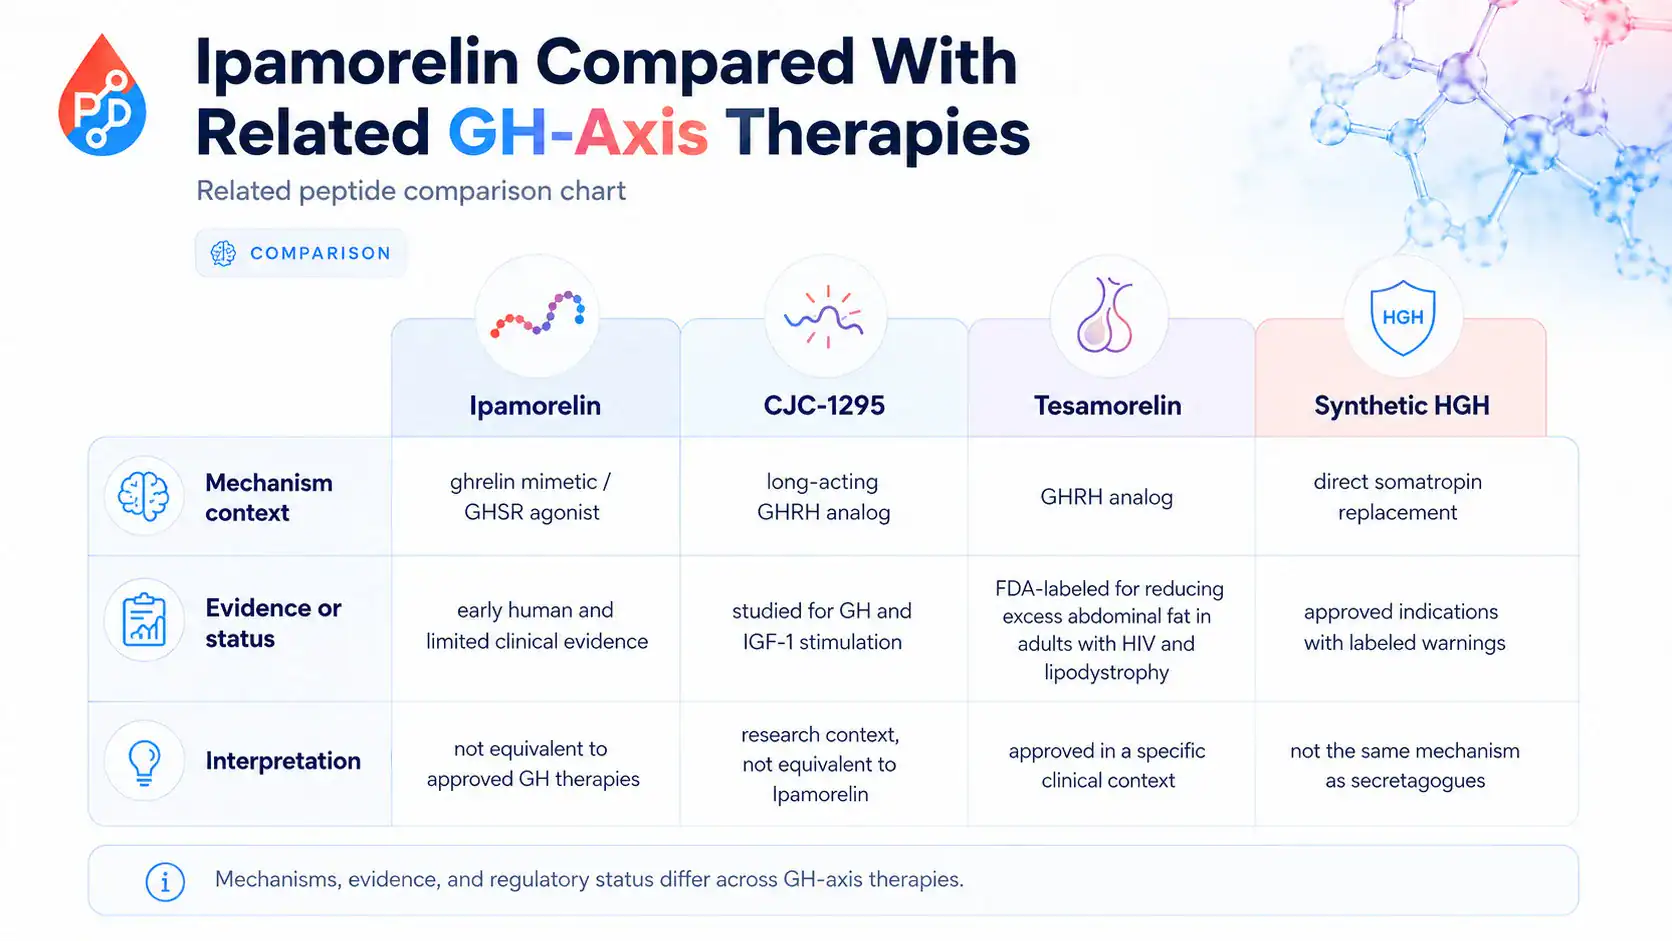
Ipamorelin differs from CJC-1295, tesamorelin, GHRP-6, and synthetic HGH by mechanism, evidence level, approval status, and clinical context 7, 15.
| Therapy or Peptide | Mechanism Context | Evidence or Status | Key Interpretation |
|---|---|---|---|
| Ipamorelin | Ghrelin mimetic and GHSR agonist 1. | Early human GH-response data and limited phase 2 clinical testing 3, 4. | Not FDA-approved; broad wellness claims are not established. |
| CJC-1295 | Long-acting GHRH analog that stimulates GH and IGF-1 15. | Human studies reported prolonged GH and IGF-1 stimulation after subcutaneous dosing 15. | Mechanistically related but not equivalent to ipamorelin. |
| Tesamorelin | GHRF analog 7. | FDA-labeled for reducing excess abdominal fat in adults with HIV and lipodystrophy 7. | Approved for a specific indication, not general weight loss. |
| Synthetic HGH | Direct somatropin replacement 8. | Approved for specific pediatric and adult indications, with contraindications and warnings 8. | Different mechanism and regulatory status from secretagogues. |
Full View
CJC-1295 and Ipamorelin as a Peptide Combination
CJC-1295 and ipamorelin are often discussed as a peptide combination because CJC-1295 acts through the GHRH side of the axis, while ipamorelin acts through GHSR signaling. A controlled study of CJC-1295 reported sustained dose-dependent GH and IGF-1 increases after subcutaneous administration in healthy adults 15.
Combination logic is mechanistic, not proof of clinical benefit. Combining two GH-axis agents could also increase monitoring complexity and risk.
Tesamorelin and Approved-Drug Comparison Points
Tesamorelin is a GHRF analog with FDA-labeled use for reduction of excess abdominal fat in adults with HIV and lipodystrophy 7. Its label also states that long-term cardiovascular safety has not been established and that tesamorelin is not indicated for weight loss management 7.
This comparison helps readers understand regulatory evidence. Tesamorelin has approved labeling for a specific population and indication; ipamorelin does not.
Synthetic HGH Versus Secretagogue Approaches
Synthetic HGH, such as somatropin, provides exogenous growth hormone. Secretagogues such as ipamorelin stimulate endogenous GH release through receptor-mediated signaling 1, 8.
The safety frameworks differ, but both involve the GH and IGF-1 axis. That is why contraindications, glucose effects, malignancy history, and endocrine diagnosis matter.
What Is the FDA, Compounding, and Regulatory Status?
Ipamorelin is not an FDA-approved drug in the United States, and FDA compounding materials identify ipamorelin acetate among bulk substances with significant safety concerns 5, 6.
Is Ipamorelin Peptide FDA-Approved?
Ipamorelin peptide is not FDA-approved for growth hormone deficiency, postoperative ileus, body composition, fat loss, anti-aging, muscle growth, sleep, or wellness use. FDA PCAC materials state that neither ipamorelin acetate nor ipamorelin free base is a component of an FDA-approved drug and that there is no USP or NF monograph for the substances 5.
For athletes, regulatory context extends beyond FDA status. The World Anti-Doping Agency’s 2026 Prohibited List includes growth hormone secretagogues such as ipamorelin under prohibited substances 17.
Compounding Pharmacies and Unapproved Peptide Concerns
FDA’s Category 2 compounding page lists ipamorelin acetate under substances that may present significant safety risks, citing immunogenicity, aggregation, peptide-related impurities, unnatural amino acids, serious adverse events including death with IV use for gastric motility, and lack of safety information for other injectable routes 6.
Regulatory status matters because approved medicines are evaluated for a specific indication, dose, route, label, manufacturing quality, and risk profile. Unapproved peptide use does not have the same evidentiary or regulatory foundation.
What Evidence Gaps and Clinician Discussion Points Remain?
The biggest evidence gaps for ipamorelin involve long-term safety, outpatient use, body composition outcomes, anti-aging claims, product quality, dose standardization, and comparative benefit versus approved alternatives 5, 6, 12.
What Remains Unknown About Long-Term Safety?
Long-term safety of ipamorelin remains unclear because the available human evidence is narrow, and FDA reviewers noted a lack of clinical studies adequately assessing immunogenicity, aggregation-related risk, and proposed subcutaneous administration 5.
Unknowns include repeated-use effects on IGF-1, glucose metabolism, edema, tissue growth, malignancy risk, cardiovascular outcomes, fertility-related hormones, and interactions with other endocrine therapies. These gaps should weigh heavily in any clinical discussion.
Questions to Discuss Before Any Peptide Therapy
A clinician discussion about ipamorelin should focus on diagnosis, evidence, risks, alternatives, monitoring, and regulatory status rather than on internet protocols.
Practical checklist for a clinician conversation:
- Is there a confirmed endocrine diagnosis, such as adult growth hormone deficiency, that warrants formal evaluation?
- Are symptoms being attributed to low GH actually explained by sleep disorders, medications, thyroid disease, nutrition, depression, stress, or another condition?
- What is the evidence level for the intended outcome: approved use, clinical evidence, early human evidence, preclinical evidence, or unsupported claim?
- What are the risks related to glucose metabolism, cancer history, pituitary disease, cardiovascular history, pregnancy, breastfeeding, or current medications?
- Are approved alternatives, such as labeled GH therapies or tesamorelin for its specific indication, more appropriate to discuss?
- What monitoring would be needed for IGF-1, glucose, adverse effects, and clinical response?
- How does regulatory status affect product quality, sterility, dose accuracy, and legal risk?
The safest way to interpret ipamorelin peptide is through evidence quality, regulatory status, safety data, and clinician-guided decision-making. The strongest conclusions come from approved labeling and controlled human studies; weaker claims about fat loss, muscle growth, sleep, recovery, and anti-aging should be treated cautiously.
Related dosage protocols and research
Use the available links to move between research context, dosage pages or comparisons, and supporting guides. When vial-size variants exist, they remain separate because concentration and syringe-unit calculations change with vial strength. Comparisons do not imply that different compounds are interchangeable.
Matching dosage protocols
Related protocols and comparisons
- CJC-1295 NO DAC + Ipamorelin (10 mg Blend) Dosage Protocol
- Tesamorelin 5mg + Ipamorelin 5mg (10mg Blend) Dosage Protocol
- CJC-1295 DAC (5 mg) + Ipamorelin (5 mg) Stack Dosage Protocol
- CJC-1295 DAC (2 mg) + Ipamorelin (5 mg) Stack Dosage Protocol
- AOD-9604 + CJC-1295 + Ipamorelin (12 mg Blend) Dosage Protocol
Further research context
- What Is GHRP-2? Mechanism, Benefits, Risks, and Alternatives
- GHRP-6 Peptide: Benefits, Uses, Side Effects, Dosage, and Research
- Sermorelin Peptide: Benefits, Uses, Side Effects, Dosage, and Research
Core guides
References
Ipamorelin
cancer.gov
1
Ipamorelin, the first selective growth hormone secretagogue
pubmed.ncbi.nlm.nih.gov
2
Pharmacokinetic-Pharmacodynamic Modeling of Ipamorelin, a Growth Hormone Releasing Peptide, in Human Volunteers
link.springer.com
3
Prospective, randomized, controlled, proof-of-concept study of the ghrelin mimetic ipamorelin for the management of postoperative ileus in bowel resection patients
link.springer.com
4
October 29, 2024 Meeting of the Pharmacy Compounding Advisory Committee: Ipamorelin-related bulk drug substances
fda.gov
5
Certain Bulk Drug Substances for Use in Compounding that May Present Significant Safety Risks
fda.gov
6
EGRIFTA SV—tesamorelin kit
dailymed.nlm.nih.gov
7
GENOTROPIN—somatropin kit
dailymed.nlm.nih.gov
8
ALVIMOPAN capsule
dailymed.nlm.nih.gov
9
Evaluation and Treatment of Adult Growth Hormone Deficiency
endocrine.org
10
Adult Growth Hormone Deficiency—Clinical Management
ncbi.nlm.nih.gov
11
The Safety and Efficacy of Growth Hormone Secretagogues
pubmed.ncbi.nlm.nih.gov
12
Efficacy of ipamorelin, a ghrelin mimetic, on gastric dysmotility in a rodent model of postoperative ileus
pubmed.ncbi.nlm.nih.gov
13
Ipamorelin, a new growth-hormone-releasing peptide, induces longitudinal bone growth in rats
pubmed.ncbi.nlm.nih.gov
14
Prolonged Stimulation of Growth Hormone and Insulin-Like Growth Factor I Secretion by CJC-1295, a Long-Acting Analog of Growth Hormone-Releasing Hormone, in Healthy Adults
academic.oup.com
15
Ipamorelin Completed Phase 2 Trials for Ileus Treatment
go.drugbank.com
16
2026 Prohibited List
wada-ama.org
17
FAQs
What is Ipamorelin peptide used for?
Ipamorelin peptide is mainly discussed as an investigational growth hormone secretagogue, not as an FDA-approved treatment. Published research has examined its ability to stimulate growth hormone release and its possible role in postoperative ileus, but it is not approved for wellness, anti-aging, fat loss, muscle growth, or sleep improvement 1, 4, 5. Therapeutic use should be interpreted through clinical evidence, regulatory status, and clinician-guided evaluation.
How does Ipamorelin work?
Ipamorelin works by mimicking ghrelin signaling at the growth hormone secretagogue receptor, which can stimulate growth hormone release from the pituitary gland 1, 2. This mechanism may affect GH and IGF-1 signaling, but a hormone response does not automatically prove improved patient outcomes. Claims about natural growth hormone production, body composition, recovery, or metabolism need evidence grading rather than assumption.
What are the potential benefits of Ipamorelin therapy?
Potential benefits of Ipamorelin therapy are usually described around GH release, body composition, recovery, sleep, metabolism, and healthy aging, but most broad benefit claims remain evidence-limited. Early human studies measured GH response, while a postoperative ileus trial tested a specific clinical setting 3, 4. Claims that it can improve body composition, healing, or sleep should be treated as preliminary unless supported by stronger human studies.
What side effects or downsides can Ipamorelin cause?
Side effects and downsides of Ipamorelin may include study-reported adverse events, hormone-related risks, and uncertainty around unapproved or compounded products. FDA review materials discussed concerns such as glucose intolerance, tissue growth, neoplasms, cardiovascular effects, immunogenicity, aggregation, and peptide impurities 5, 6. Injection-site reactions, allergic reaction risk, and incomplete long-term safety data should be discussed with a licensed clinician.
How is Ipamorelin administered, and what dosage information exists?
Ipamorelin administration and dosage information should be understood from published studies, not as a personal protocol. Human research has used monitored intravenous dosing, including a postoperative ileus study using 0.03 mg/kg twice daily in a hospital setting 4. FDA materials also discussed proposed subcutaneous injection but noted limited safety data for that route 5. Dose, route of administration, and monitoring depend on clinical context.
Is Ipamorelin safe and FDA-approved?
Ipamorelin is not FDA-approved, and its safety is not established for general peptide therapy, body composition, anti-aging, or wellness use 5, 6. Regulatory status matters because approved and unapproved peptides are evaluated differently for indication, manufacturing quality, dosing, labeling, and safety. Readers should ask a clinician about contraindications, drug interactions, diagnosis, approved alternatives, and whether the evidence supports the intended clinical use.
Researchers Cited in This Article
The researchers below authored or co-authored publications cited in this article. Listing them here identifies sources; it does not mean they wrote, independently reviewed, sponsored, or endorsed this PeptideDosages.com article. The site author is identified in the article byline.
Kirsten Raun
Researcher profile: Google Scholar
Kirsten Raun is a scientific author whose published work is directly relevant to the pharmacology of Ipamorelin peptide and related growth hormone secretagogue research. Her publications help frame the article’s discussion of ghrelin-receptor activity, GH release, selectivity, and the distinction between early pharmacology findings and broader therapeutic claims. The selected studies are useful for understanding Ipamorelin’s original characterization and the wider development of related GH secretagogue compounds.
Selected publications:
- Ipamorelin, the first selective growth hormone secretagogue — European Journal of Endocrinology, 1998. PMID: 9849822
- Pharmacological characterisation of a new oral GH secretagogue, NN703 — European Journal of Endocrinology, 1999. PMID: 10427162
Joga Gobburu
Researcher profile: University of Maryland School of Pharmacy
Joga Gobburu is a published pharmacometrics and clinical pharmacology author whose work is relevant to the article’s interpretation of Ipamorelin pharmacokinetics, pharmacodynamics, dose-response context, and evidence limitations. His Ipamorelin publication directly examined PK/PD modeling in human volunteers, while his broader modeling work provides context for interpreting drug, dose, and trial evidence without converting study protocols into personal medical recommendations.
Selected publications:
- Pharmacokinetic-pharmacodynamic modeling of ipamorelin, a growth hormone releasing peptide, in human volunteers — Pharmaceutical Research, 1999. PMID: 10496658
- Quantitative disease, drug, and trial models — Annual Review of Pharmacology and Toxicology, 2009. PMID: 18851702
Evidence: Claim-level sources are linked·Editorial standards & correctionsPrevious ArticleAOD-9604 Peptide: Benefits, Uses, Side Effects, Dosage, and ResearchNext ArticleIGF-1 LR3 Peptide: Benefits, Uses, Side Effects, Dosage, and Research