
CJC-1295 DAC (5 mg) + Ipamorelin (5 mg) Stack Dosage Protocol
- Table of Contents
- CJC-1295 DAC Dosage Chart
- Dosing & Reconstitution Guide
- CJC-1295 DAC (5 mg Vial) — Subcutaneous, Once Weekly
- CJC-1295 DAC Reconstitution Steps
- Ipamorelin (5 mg Vial) — Subcutaneous, Once Daily
- Ipamorelin Reconstitution Steps
- Combined Stack Schedule — Standard Approach
- Supplies Needed
- Protocol Overview
- Dosing Protocol
- Storage Instructions
- Important Notes
- How This Works
- Potential Benefits & Side Effects
- Lifestyle Factors
- Injection Technique
- References
- Additional Research and Background
CJC-1295 DAC Dosage Chart
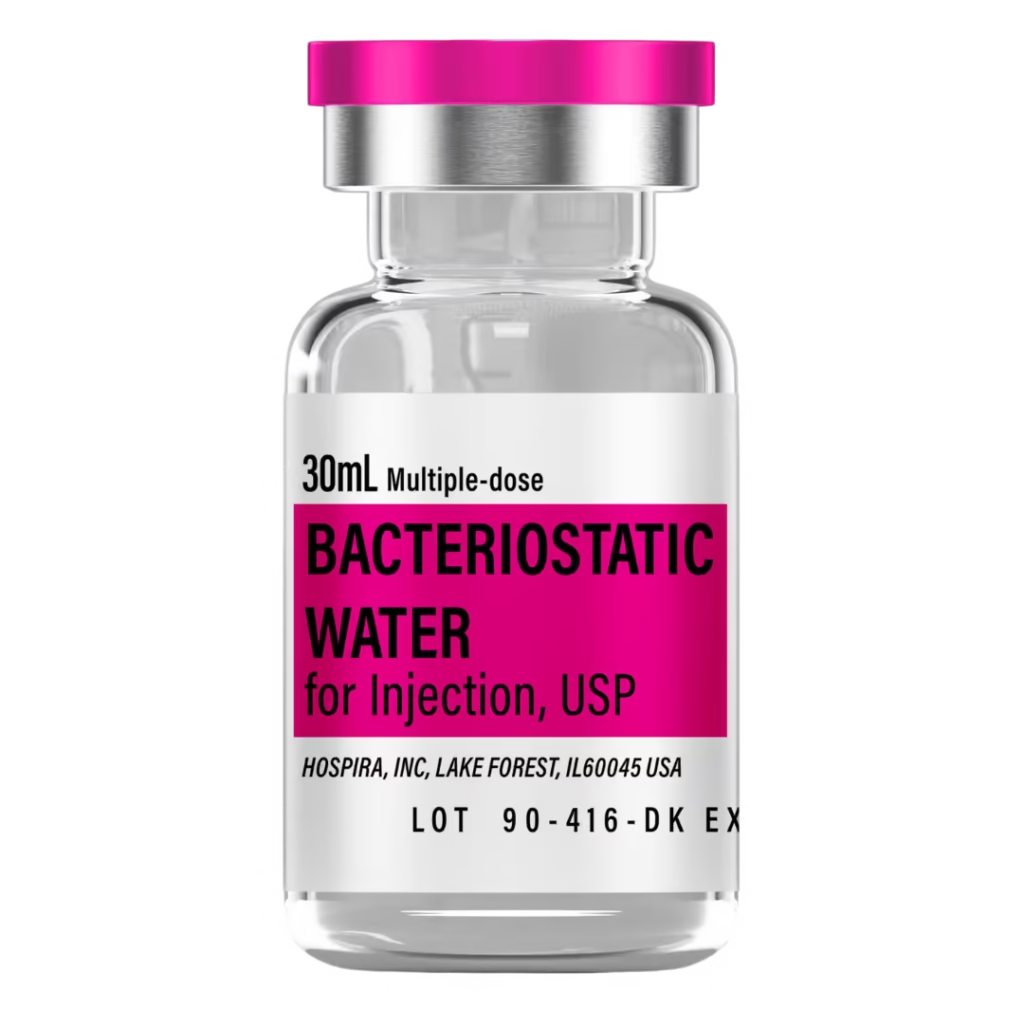
CJC-1295 DAC is dosed at 1 mg–2 mg weekly via subcutaneous injection in educational protocols. A 5 mg reconstituted with bacteriostatic water yields about 2.5 mg/mL. This information is for research and educational use only.
- CJC-1295 DAC: Add 2.0 mL bacteriostatic water → 2.5 mg/mL; inject once weekly.
- Ipamorelin: Add 3.0 mL bacteriostatic water → 1.67 mg/mL; inject once daily.
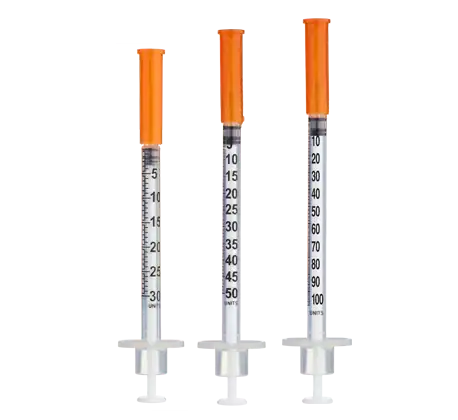
- Easy measuring: CJC-1295 DAC: 1 unit = 25 mcg; Ipamorelin: 1 unit ≈ 16.7 mcg on U-100 syringes.
- Storage: Lyophilized: ≤−15 °C (5 °F); reconstituted: 2–8 °C (35.6–46.4 °F); use within 3–4 weeks[5].

This stacked protocol combines CJC-1295 DAC, a long-acting GHRH analog with extended half-life via albumin binding[1], and Ipamorelin, a selective ghrelin-receptor agonist that triggers potent GH pulses with minimal ACTH/cortisol release[2]. Together, these peptides amplify endogenous growth hormone secretion and IGF-1 signaling through complementary mechanisms[3].
Related research: For distinct compound, component, or formulation evidence and safety context, read Ipamorelin Peptide: Benefits, Uses, Side Effects, Dosage, and Research and CJC-1295 DAC Peptide: Benefits, Uses, Side Effects, Dosage, and Research. These links are comparisons only; the compounds and formulations should not be treated as interchangeable.
Dosing & Reconstitution Guide
Educational guide for stacked GH secretagogue protocol
CJC-1295 DAC (5 mg Vial) — Subcutaneous, Once Weekly
Reconstitution: 2.0 mL bacteriostatic water → 2.5 mg/mL (2500 mcg/mL) → 25 mcg per unit
Phase
Weekly Dose (mcg / mg)
Units (mL) per Injection
Units (per injection) (mL)
Standard
1000 mcg (1.0 mg)
40 units (0.40 mL)
Once weekly
Aggressive
2000 mcg (2.0 mg)
80 units (0.80 mL)
Once weekly
Note: At 2.5 mg/mL, each 5 mg vial provides 2.5 standard doses (1 mg each) or 1.25 aggressive doses (2 mg each).
CJC-1295 DAC Reconstitution Steps
- Draw 2.0 mL bacteriostatic water with a sterile syringe.
- Inject slowly down the vial wall; avoid foaming or direct stream onto powder.
- Gently swirl/roll until fully dissolved (do not shake).
- Label with date and refrigerate at 2–8 °C (35.6–46.4 °F).
amorelin (5 mg Vial) — Subcutaneous, Once Daily
Reconstitution: 3.0 mL bacteriostatic water → 1.67 mg/mL (1666.7 mcg/mL) → 16.67 mcg per unit
Phase
Daily Dose (mg)
Units (mL) per Injection
Frequency
| Weeks 1–2 (Initiation) | 100 mcg (0.1 mg) | 6 units (0.06 mL) | Once daily |
| Weeks 3–4 (Titration) | 150 mcg (0.15 mg) | 9 units (0.09 mL) | Once daily |
| Weeks 5+ (Maintenance) | 200 mcg (0.2 mg) | 12 units (0.12 mL) | Once daily |
| Aggressive (Optional) | 300 mcg (0.3 mg) | 18 units (0.18 mL) | Once daily or split 2×/day |
For ≤10-unit (≤0.10 mL) administrations, consider 30- or 50-unit insulin syringes for improved readability.
Ipamorelin Reconstitution Steps
- Draw 3.0 mL bacteriostatic water with a sterile syringe.
- Inject slowly down the vial wall; avoid foaming.
- Gently swirl/roll until dissolved (do not shake).
- Label with date and refrigerate at 2–8 °C (35.6–46.4 °F).
Combined Stack Schedule — Standard Approach
Week
CJC-1295 DAC (Weekly)
Ipamorelin (Daily)
| Weeks 1–2 | 1000 mcg (40 units) once weekly | 100 mcg (6 units) once daily |
| Weeks 3–4 | 1000 mcg (40 units) once weekly | 150 mcg (9 units) once daily |
| Weeks 5–12 | 1000 mcg (40 units) once weekly | 200 mcg (12 units) once daily |
Timing: CJC-1295 DAC is typically administered on a fixed day each week. Ipamorelin is commonly administered before bed to coincide with natural nocturnal GH pulses[4].
Important: This guide is for therapeutic educational purposes only and does not constitute medical advice, diagnosis, or treatment.
Supplies Needed
Plan based on an 8–16 week stacked protocol with standard dosing (CJC-1295 DAC 1 mg/week + Ipamorelin 200 mcg/day at maintenance).
- CJC-1295 DAC Vials (5 mg each):
- 8 weeks (8 mg total) → 2 vials
- 12 weeks (12 mg total) → 3 vials
- 16 weeks (16 mg total) → 4 vials
- Ipamorelin Vials (5 mg each):
- 8 weeks (56 days at ~200 mcg/day) → 3 vials
- 12 weeks (84 days) → 4 vials
- 16 weeks (112 days) → 5 vials
- Insulin Syringes (U-100):
- Per week: 1 (CJC) + 7 (Ipamorelin) = 8 syringes
- 8 weeks: 64 syringes
- 12 weeks: 96 syringes
- 16 weeks: 128 syringes
- For Ipamorelin doses ≤10 units, 30- or 50-unit syringes improve accuracy.
- Bacteriostatic Water (10 mL bottles):
- 8 weeks: CJC (2 × 2 mL = 4 mL) + Ipam (3 × 3 mL = 9 mL) = 13 mL → 2 × 10 mL bottles
- 12 weeks: CJC (3 × 2 mL = 6 mL) + Ipam (4 × 3 mL = 12 mL) = 18 mL → 2 × 10 mL bottles
- 16 weeks: CJC (4 × 2 mL = 8 mL) + Ipam (5 × 3 mL = 15 mL) = 23 mL → 3 × 10 mL bottles
- Alcohol Swabs:
- Per week: ~16 swabs (2/day for Ipamorelin + 2 for CJC weekly)
- 8 weeks: 128 swabs → 2 × 100-count boxes
- 12 weeks: 192 swabs → 2 × 100-count boxes
- 16 weeks: 256 swabs → 3 × 100-count boxes


Protocol Overview
Concise summary of the stacked GH secretagogue regimen.
- Goal: Amplify endogenous GH/IGF-1 secretion through dual GHRH and ghrelin-receptor pathways[3].
- Schedule: CJC-1295 DAC once weekly + Ipamorelin once daily for 8–16 weeks.
- CJC-1295 DAC Dose: 1–2 mg weekly (standard: 1 mg).
- Ipamorelin Dose: 100–300 mcg daily with gradual titration.
- Storage: Lyophilized frozen; reconstituted refrigerated; avoid freeze–thaw cycles.
Dosing Protocol
Suggested approach for the stacked regimen.
- CJC-1295 DAC: 1 mg (40 units) subcutaneously once per week on a consistent day.
- Ipamorelin: Start at 100 mcg (6 units) daily; titrate to 200 mcg (12 units) by Week 5.
- Timing: Ipamorelin before bed aligns with natural nocturnal GH release[4].
- Cycle Length: 8–12 weeks standard; extend to 16 weeks if tolerated.
- Injection Sites: Rotate abdomen, thighs, and upper arms.
Storage Instructions
Proper storage preserves peptide integrity and efficacy.
- Lyophilized (dry powder): Store at ≤−15 °C (5 °F); preferably ≤−50 °C (−58 °F) for long-term storage[5].
- Reconstituted: Refrigerate at 2–8 °C (35.6–46.4 °F); use within 3–4 weeks[6].
- Allow vials to reach room temperature before opening to minimize condensation uptake.
- Avoid repeated freeze–thaw cycles of reconstituted solutions.
Important Notes
Practical considerations for consistency and safety.
- Use a new sterile insulin syringe for each injection; dispose in a sharps container.
- Rotate injection sites systematically (abdomen, thighs, upper arms) to reduce local irritation.
- Inject slowly; wait a few seconds before withdrawing the needle.
- Document daily Ipamorelin doses and weekly CJC-1295 DAC administrations to maintain consistency.
- Keep CJC-1295 DAC and Ipamorelin in separate vials; do not pre-mix.
How This Works
CJC-1295 DAC functions as a synthetic GHRH analog that stimulates pituitary GH release. Its Drug Affinity Complex (DAC) moiety binds to serum albumin, extending its half-life to approximately 6–8 days and producing sustained, dose-dependent elevations in GH and IGF-1[1]. Ipamorelin is a selective growth hormone secretagogue that activates the ghrelin receptor (GHSR) to trigger rapid GH pulses without significantly affecting ACTH, cortisol, or prolactin[2]. When combined, these peptides act through complementary pathways—GHRH receptor and ghrelin receptor—to synergistically amplify endogenous GH secretion[3].
Potential Benefits & Side Effects
Observations from preclinical and clinical literature on GH secretagogues.
- Body composition: GH secretagogues have demonstrated improvements in lean mass and reductions in fat mass in clinical studies[7].
- Sustained GH/IGF-1 elevation: CJC-1295 DAC produces prolonged elevations lasting 6–11 days per administration[1].
- Selectivity: Ipamorelin does not significantly increase cortisol or ACTH at therapeutic doses[2].
- Tolerability: Both peptides were well tolerated in human studies, with transient injection-site reactions being the most common adverse effect[8].
- Water retention, mild headache, and transient numbness/tingling have been reported with GH-elevating compounds.
Lifestyle Factors
Complementary strategies for optimal outcomes.
- Pair with a balanced, protein-forward diet tailored to individual energy and recovery needs.
- Combine resistance training and aerobic activity to support anabolic adaptations.
- Prioritize 7–9 hours of quality sleep; GH secretion peaks during deep sleep[4].
- Manage stress and avoid chronic caloric restriction, which can blunt GH response.
Injection Technique
General subcutaneous guidance from clinical best-practice resources[9].
- Clean the vial stopper and skin with alcohol; allow to dry completely.
- Pinch a skinfold; insert the needle at 45–90° into subcutaneous tissue[9].
- Do not aspirate for subcutaneous injections; inject slowly and steadily[10].
- Rotate sites systematically (abdomen, thighs, upper arms) to avoid lipohypertrophy.
- Limit each injection to ≤1 mL; split larger volumes into separate injections[9].
Important Note
This content is intended for therapeutic educational purposes only and does not constitute medical advice, diagnosis, or treatment.
References
Journal of Clinical Endocrinology & Metabolism
— Prolonged stimulation of GH and IGF-I secretion by CJC-1295 in healthy adults
European Journal of Endocrinology
— Ipamorelin, the first selective growth hormone secretagogue
Endocrine Reviews
Growth hormone secretagogues: mechanisms and clinical applications
Sleep Medicine Reviews
— Sleep and the GH/IGF-1 axis: physiological and clinical implications
Bachem
— Reconstituted peptide storage and stability recommendations
Translational Andrology and Urology (PMC)
— GH secretagogues in body composition management for hypogonadal males
International Journal of Surgery (PubMed)
The parameter is incorrect.Image size is not supported. Each image dimension must be between 40 and 2600 pixels.
NCBI Bookshelf
— Parenteral medication administration: subcutaneous injection technique
CDC
— Vaccine administration guidelines: subcutaneous route (no aspiration required)
Additional Research and Background
These sources provide related context and are not presented as support for a specific statement above.
Growth Hormone & IGF Research (ScienceDirect)
— Ipamorelin induces longitudinal bone growth in rats
Physiological Reviews
The somatotropic axis: GH and IGF-1 regulation and actions
Clinical Drug Investigation (PMC)
— Subcutaneous drug delivery: pharmacokinetic considerations
Related research, protocols, and guides
Explore the available research context, protocol variants or comparisons, and practical guides. When vial-size variants exist, they remain separate because vial strength, concentration, and syringe-unit calculations can differ. Related compounds and blends are comparisons only, not interchangeable.
Other vial-size protocols
Evidence: Dosing and safety sources are linked·Editorial standards & corrections